
In this procedure a simultaneous uplift and breast enlargement is performed.
0151 433 0775


In this procedure a simultaneous uplift and breast enlargement is performed.
The mastopexy (breast uplift) lifts and tightens the breasts, and the enlargement increases their volume. It is therefore a useful procedure in patients who feel that they have a lot of breast sag (ptosis) but also lack volume. This can commonly occur, for example, after pregnancy. It is also a useful procedure for patients who have breast asymmetry.
As combing the procedures does carry a greater risk than the individual operations, if someone can get away with “just a lift” or “just an augmentation”, it may be better to do that and reduce the risk, and if necessary do the other procedure as a second stage.


This lady in her mid-50s had breasts which she felt lacked fullness and had too much sag, and a small degree of asymmetry. This was managed with a combined breast augmentation over the muscle, and a breast uplift.
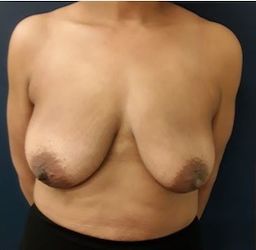

This lady in her late 40s had breasts that she felt lacked fullness and had significant sag (ptosis). Only lifting would have left inadequate volume, so this was managed with a combined breast augmentation over the muscle, and a breast uplift.

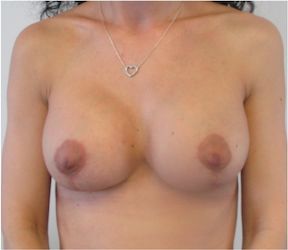
Following children, this lady in her mid 30s had breasts that she felt lacked fullness and had significant sag (ptosis). She was also bothered by the asymmetry, which mainly affected the fold underneath the breasts (the “inframammary fold”). This was managed with a combined breast augmentation partially under the muscle (”dual plane”), and a breast uplift.
There is a group of patients who, following breast augmentation, feel that they are generally tired, may get muscle aches or generally not feel great. The collection of these and other non-specific symptoms has been called “breast implant illness”. It is a controversial subject as from a medical point of view there is disagreement on how exactly to diagnose it, with some experts feeling it is not an actual condition. This of course does not mean that breast implant illness is not real or that it does not exist – rather it is a reflection of the fact that our understanding of the matter is currently still developing . The treatment for it has been suggested to be removal of the implants with or without their capsules, however, that is again controversial, as the procedure itself carries risks, and as yet the benefits remain uncertain. More information and time will hopefully clarify this difficult subject further.
Whenever an artificial material is put into the body, the body “walls it off” by making scar tissue around it. Around a breast implant, we call this a capsule and it develops within a few short weeks after surgery. This process is quite normal. What is not normal is when that capsule tightens down and becomes painful or changes the shape of the implants, in which case we call it capsular contracture. In textured implants under the muscle, around 3.5% of women will have this within 10 years and with smooth about 5%. The rates, particularly with smooth implants, are much higher over the muscle.
Perhaps more than any other operation, breast augmentation generates uncertainty about what option to go for. Smooth or Textured implants? Teardrop ("anatomical") or round? And so on. In the end, there is no one-size-fits-all answer, and the plan needs to be tailored to the individual patient and their needs.
Below is a list of common dilemmas patients face about breast augmentations along with my thoughts on them.
Over the muscle vs under the muscle - Breast implants placed over the pectoral muscle (sub-glandular) have the advantage of often giving more “fullness” and minimising the damage to the muscle. However, they can also, therefore, look more “fake” than under the muscle or dual plane. Furthermore, there is a greater risk of capsular contracture over the muscle (internal scar tissue that can cause pain and deformity) especially with smooth implants. Under the pectoral muscle, implants tend to be less “fake”, but similarly may look less “full” than over the muscle. Going under the muscle also means having to partially cut the muscle, though I have not seen any long-term functional consequence to this, a risk of the implants moving around as the muscle contracts ("implant animation"). In general, I would tend to put implants as under the muscle/dual plane where I think going over the muscle would look too fake.
Under the muscle vs dual plane - Technically speaking “under the muscle” means that the entire breast implant is completely covered by muscle. Dual plane basically means the top of the implant is covered by the muscle and the bottom bit is under the gland (so it’s a bit under and and bit not!). It has the advantage of hiding the “fakeness” of the implants and of allowing the lower part of the implant to expand out the lower pole. From a risk profile point of view, it is similar to under the muscle. In general, I find if choosing between under the muscle and dual plane, I get a better result from dual plane, though there are of course exceptions.




Renacres Hospital,
Renacres Ln,
Halsall,
Ormskirk
L39 8SE
info@pundriquesharma.co.uk
0151 433 0775
© 2025 Pundrique Sharma Plastic Surgeon
Website by beachshore